Apparently, Some Things Really Do Run in the Family

I traveled down some very familiar roads last week, Thursday September 24th, and learned a little more about a woman I never really had the chance to know.

My great-grandmother Bertie (Bertha Mae Ransom Thompson, for those of you who may have had her on your great grandparents birth records and are armchair geneaologists,) was a homebirth midwife, dedicated to serving other women. I learned that she was also known for being brutally frank.

Well.

Apparently some things really do run in the family.

Then I looked more closely at the old photographs of her and realized something else.

Annie Hill outdoors beside a wooded lake.
I looked a little tired, but I’d been traveling a bit with more to come ahead…

I have her eyes.

I can’t quite explain how comforting that is. The same eyes, a bit of the same attitude, and generations apart, the same calling to serve women.

So, in the very brief time I had before I needed to return to Arkansas, where we’ve become very busy, I had the chance to sit beside the AuSable River in Mio, Michigan, and reflect.

I will gladly remain brutally frank if it means giving women the chance to have informed consent and to be in the driver’s seat for their pregnancy, birth, and postpartum experience.

Brutally frank doesn’t mean unkind.

Sometimes it means saying what needs to be said. Sometimes it means asking the question no one else has asked. Sometimes it means making sure a woman understands that she has choices, that her questions matter, and that her voice belongs in the room.

It means being what she needs, whatever that is, to help make sure her needs are heard and respected during this transformative time of life.

And then there’s another part of this story that makes it even more meaningful to me.

Portrait of Paula Branam.My cousin Paula Branam has the same great-grandmother.  Yes, that Paula here at Bright Blessings.

And Paula seems every bit as driven to care for women, particularly during the postpartum segment of their childbearing journey.

Now I have the privilege of having her learn from me as she prepares for her own work as a doula.

There is something deeply meaningful about that.

Bertie could never have known where her work would lead. She couldn’t have known that generations later, two of her great-granddaughters would find themselves drawn to caring for women and families.

More than a hundred years ago, Bertie served women in her community as a midwife.

Today, I’m still doing the work.  Back at my desk in Arkansas, less than a week later, as I prepare for the doula training program to launch, for the upcoming Doula Conference for the Doula Alliance of Arkansas,  and continue to work on health care credentialling – which means signing contracts to be in network with insurance providers here in Arkansas.

And now I get to teach Paula some of what I’ve learned, while both of us, in our own ways, honor the woman who came before us.

Different generations. Different kinds of birthwork. Different communities.

But that same thread keeps running through our family.

Same eyes.

Same calling.

And another generation carrying it forward.

I think our great-grandmother would have been pretty pleased by that, too.

Social media didn’t create distrust in maternity care. It gave it a microphone.

Good morning, Annie here.

My day frequently starts before I ever crawl out of bed.

Sometimes it is a text that came in overnight. Sometimes it is something I see on social media. Sometimes something lands in front of me that touches a subject I care deeply about, and suddenly I am working before my feet have even touched the floor.

That is pretty normal for me.

Also pretty normal for me? Getting passionate about something and accidentally writing a small novel about it.

So I apologize in advance for the novel-length post.

I felt strongly enough about this one that I wanted to take the time to write it. I would love for you to read it if you have the time. I also completely understand if your morning does not have room for one of Annie’s accidental dissertations about maternity care.

This morning, a Reel about epidurals, Pitocin, evidence-based medicine, social media, birth plans, and patient trust got my brain going.

And here’s the frustrating part:

I agreed with quite a bit of it.

Evidence matters.

Clinical education matters.

Experience matters.

Having a large social media following does not make someone a medical expert.

A video telling every pregnant person to refuse Pitocin, refuse an epidural, refuse an induction, or refuse some other intervention is not individualized care.

Birth plans are not scripts. Circumstances change.

Pitocin has legitimate medical uses.

Epidurals are a valuable form of pain relief for many people.

Sometimes the safest birth looks very different from the birth somebody envisioned during pregnancy.

And evidence-based medicine absolutely must allow for individual patient circumstances and nuance.

Yes.

Exactly.

But that last sentence is also where I start getting frustrated.

The patient is part of the nuance

“Individual patient circumstances and nuance” cannot refer only to a diagnosis, a fetal monitor strip, laboratory results, medication protocols, or what generally happens on a particular labor and delivery unit.

The individual patient is actually in there somewhere.

Her circumstances include her medical history.

They also include her previous experiences.

Her fears.

Her values.

Her cultural and family history.

What happened during her last birth.

What makes her feel safe.

What makes her feel vulnerable.

How she experiences pain.

What she has already told us matters to her.

And what information she needs before she is comfortable making a decision.

The patient experience is part of the nuance.

That does not compete with evidence-based medicine.

It is part of it.

Evidence-based medicine has never meant research evidence alone. It brings together the best available evidence, clinical expertise, and the individual patient’s values and circumstances.

ACOG’s own guidance on informed consent and shared decision-making describes care in much the same way: risks and benefits should be considered within the context of the patient’s values and priorities.

ACOG: Informed Consent and Shared Decision Making in Obstetrics and Gynecology

TikTok did not invent this distrust

If thousands upon thousands of women are talking with one another about feeling frightened, pressured, dismissed, inadequately informed, unheard, or traumatized during maternity care, eventually we have to ask something besides:

“Who on social media is teaching women not to trust doctors?”

We also need to ask:

“Why was there enough distrust for that message to resonate in the first place?”

Because this conversation did not begin with TikTok.

It did not begin with Instagram.

It did not begin when Facebook Reels became a thing.

Some of us are old enough to remember women having these same conversations on AOL boards, email lists, message boards, pregnancy forums, and early online communities.

And before the internet?

Women told their birth stories around kitchen tables.

They talked in childbirth classes.

They talked at church.

They talked at work.

They talked to sisters, mothers, aunts, neighbors, and friends.

Women have always told one another about birth.

They talked about beautiful births.

They also talked about traumatic ones.

They talked about epidurals that did not give them the experience or relief they expected.

They talked about difficult inductions.

They talked about feeling pressured into interventions.

They talked about not understanding what had happened until afterward.

And they talked about not being listened to.

Social media did not invent those experiences.

It gave them a microphone.

That distinction matters.

Misinformation is real. So are the experiences underneath it.

Let me be very clear about something.

There is bad pregnancy information on social media.

There is sensationalized information.

There are people giving medical advice who are not qualified to give it.

There are blanket statements telling pregnant people never to accept an intervention that may sometimes be necessary or lifesaving.

I have a problem with that too.

A frightening TikTok is not a substitute for individualized medical advice.

But neither should we leap from “medical misinformation exists online” to “women distrust maternity care because social media frightened them.”

Those are two very different statements.

Sometimes misinformation finds an audience precisely because somebody’s previous experience has already taught her not to trust the system.

If that is happening, correcting the misinformation is important.

But so is asking why she was prepared to believe it.

We have evidence that not everyone feels heard

We do not have to rely entirely on anecdotes to know there is a problem.

In a 2023 CDC survey, about one in five mothers reported experiencing mistreatment during maternity care. The proportion was approximately 30% among Black, Hispanic, and multiracial respondents.

Nearly 45% of respondents said they had held back from asking questions or discussing concerns with their maternity-care provider.

Among the reasons women gave were worrying that their provider would think they were difficult, feeling that their provider seemed rushed, and not feeling confident that they knew what they were talking about.

CDC: Maternity Care Experiences
https://www.cdc.gov/mmwr/volumes/72/wr/mm7235e1.htm

Sit with that for a minute.

Almost half said they had held something back.

That is not a TikTok statistic.

That is a communication problem.

And it should concern every one of us who works in maternity care.

Race cannot be separated from this conversation

We also cannot talk seriously about trust in American maternity care without talking about race.

The latest national maternal mortality data available from the CDC show that in 2024, the maternal mortality rate for non-Hispanic Black women was 44.8 deaths per 100,000 live births, compared with 14.2 for non-Hispanic White women.

CDC: Maternal Mortality Rates in the United States, 2024
https://www.cdc.gov/nchs/data/hestat/hestat113.htm

Those numbers do not mean every Black woman will receive poor care.

They do not mean every White physician is biased.

They do not mean every hospital is unsafe.

But they do mean that a Black woman who knows these statistics is not irrational for asking hard questions about her care.

And there is evidence that bias can affect medical judgment.

Research has documented racial bias in pain assessment and treatment recommendations, including false beliefs about biological differences between Black and White patients among some medical trainees.

PubMed: Racial bias in pain assessment and treatment recommendations

Black and Indigenous families also bring historical, community, and individual experiences with medicine into the room with them.

Those experiences do not disappear because the clinician standing in front of them is kind, competent, and genuinely wants to help.

Trust cannot simply be demanded because somebody has MD after their name.

Modern medicine has also changed who can become pregnant

There is another piece of the maternal mortality conversation that deserves nuance.

Modern medicine has accomplished extraordinary things.

People with congenital heart disease, serious childhood illnesses, complex medical histories, and chronic conditions are surviving into adulthood, living full lives, and becoming pregnant when previous generations may not have had that opportunity or may have been advised that pregnancy was simply too dangerous.

That is one of medicine’s great successes.

It also means today’s pregnant population includes people with medical histories that can make pregnancy more complex.

That matters when we talk about maternal outcomes.

But recognizing medical complexity does not somehow erase racial disparities, failures of communication, mistreatment, or bias.

More than one thing can be true at the same time.

We should be sophisticated enough to hold all of them.

And then there are the interventions everyone argues about

Epidurals are not evil.

Pitocin is not evil.

Cesareans are not evil.

Inductions are not evil.

And an unmedicated vaginal birth is not morally superior to any of them.

Every one of those things is a tool or an outcome that may be appropriate in a particular situation.

The problem begins when maternity care is turned into competing camps.

One side says:

“Never let them do that to you.”

The other says:

“Stop listening to people online and trust your doctor.”

Neither answer leaves much room for the person actually giving birth.

What I would rather hear is:

Why is this being recommended?

What problem are we trying to solve?

What are the expected benefits?

What are the risks?

Are there alternatives?

What happens if we wait?

How urgently do we need to decide?

Those are not anti-medical questions.

They are not evidence that somebody has been poisoned against medicine by social media.

They are part of informed consent.

ACOG explicitly states that informed consent requires adequate, accurate, understandable information and the freedom to ask questions and make a voluntary choice. That choice can include accepting or declining recommended treatment.

Shared decision-making considers the risks and benefits of the available options in the context of the patient’s own values and priorities.

ACOG: Informed Consent and Shared Decision Making in Obstetrics and Gynecology

That is important.

Because autonomy does not mean automatically saying no.

Choosing the epidural can be autonomy.

Choosing Pitocin can be autonomy.

Choosing induction can be autonomy.

Changing your mind during labor can be autonomy.

Saying, “I don’t want that right now,” can also be autonomy.

The goal should never be teaching patients automatically to say no.

But neither should the goal be teaching them automatically to say yes.

This is where doulas belong in the conversation

And yes, I am going to talk about doulas.

A doula is not an obstetrician.

A doula does not diagnose.

A doula does not prescribe.

A doula does not replace a nurse.

A doula does not interpret a fetal monitor instead of the clinical team.

A doula should not tell a client that her physician is wrong or instruct her to refuse medically recommended treatment.

That is not our job.

But sometimes the person standing in the room who has spent time prenatally learning what matters to the patient is the doula.

We may know what happened during her previous birth.

We may know that one particular experience frightened her enough that she has worried about it for months.

We may know the questions she wanted to remember to ask.

We may notice when the woman who was asking questions ten minutes ago suddenly stops speaking.

We can help her remember what she wanted to know.

We can help her formulate a question.

We can help her understand that circumstances have changed and that it may be time to gather new information and make a new decision.

We can help her stay connected to the conversation when the birth she imagined is no longer the birth that is happening.

That does not make the doula the medical expert.

It means the doula brings a different kind of support to the team.

And continuous labor support itself has been studied.

A Cochrane review involving more than 15,000 women found that continuous support during labor was associated with several beneficial outcomes, with support from someone experienced and present solely to provide labor support, such as a doula, appearing particularly beneficial.

Cochrane: Continuous Support for Women During Childbirth

So when we talk about “individual circumstances and nuance,” I find it frustrating when doulas are treated as though we are inherently part of the problem.

A good doula should be helping create individualized care, not fighting against it.

A birth plan is not a contract with the universe

This is another place where I think both sides sometimes talk past one another.

Of course birth plans change.

Birth itself has never promised to follow the agenda.

A person can spend months planning an unmedicated vaginal birth and then develop preeclampsia.

A baby can show signs that change the risk calculation.

Labor can stall.

A patient can become exhausted.

Someone who swore she never wanted an epidural can decide that she wants one.

Someone who planned to avoid Pitocin can hear the reason it is being recommended and decide that it makes sense.

None of that means her birth plan “failed.”

And none of it means autonomy disappeared because circumstances changed.

When the clinical circumstances change, the conversation changes.

A changed situation should lead to a new informed decision.

The patient’s prenatal preferences do not override what she wants now.

That is the point.

The plan was never supposed to control the birth.

It was supposed to help everyone understand the person.

Trust has to be built

This is where I keep coming back.

If patients are walking into hospitals frightened and distrustful, we absolutely should correct misinformation.

But we also need to listen to where the fear came from.

Because trust is not restored by repeatedly telling people that medical professionals are the experts and therefore deserve to be trusted.

Trust is restored by being trustworthy.

It is built when patients are listened to.

When questions are answered without condescension.

When concerns are investigated rather than reflexively dismissed.

When clinicians can say, “I don’t know,” when something is genuinely uncertain.

When recommendations are explained.

When informed consent is treated as an ongoing process rather than a signature on a form.

When changing circumstances are explained instead of simply announced.

When the person in the bed remains part of the conversation about what happens to the person in the bed.

And when a patient who asks difficult questions is not immediately categorized as anti-doctor, anti-hospital, anti-science, or the latest victim of social-media hysteria.

Sometimes she is simply trying very hard to make an informed decision about one of the most consequential experiences of her life.

It should not be us versus them

At Bright Blessings, I do not want an adversarial relationship between doulas and medical professionals.

  • I do not want families taught to fear obstetricians.
  • I do not want obstetricians taught to fear doulas.
  • I do not want nurses caught somewhere in the middle.
  • That helps absolutely no one.
  • I want collaborative maternity care.
  • I want evidence-based medicine.
  • I want skilled physicians.
  • I want experienced nurses.
  • I want excellent midwives.
  • I want competent doulas who understand their scope.
  • I want patients who feel safe asking questions.
  • I want medical professionals whose expertise is respected.

And I want families to understand that respecting medical expertise and retaining autonomy over their own bodies are not opposing ideas.

Those things belong together.

We can challenge misinformation without dismissing the experiences that made people vulnerable to it.

We can celebrate extraordinary obstetric care without pretending poor obstetric care does not exist.

We can acknowledge that clinicians possess knowledge their patients do not without pretending that patients bring nothing important to the table.

We can recognize that social media sometimes spreads fear while also recognizing that it has given people a place to tell stories that previously went unheard.

And when thousands of people are telling us they do not trust the system, we can spend all of our energy trying to convince them that they are wrong.

Or we can become curious about why.

I think maternity care desperately needs more of that curiosity.

Because the solution to an “us versus them” mentality is not figuring out which side is right.

It is remembering that there shouldn’t be sides.

Sources and further reading

ACOG: Informed Consent and Shared Decision Making in Obstetrics and Gynecology

CDC: Maternity Care Experiences

CDC: Maternal Mortality Rates in the United States, 2024

PubMed: Racial bias in pain assessment and treatment recommendations

Cochrane: Continuous Support for Women During Childbirth

Related: Meet the Bright Blessings team and explore our birth doula support.

YOU’RE NOT IN THE MILITARY. STOP USING SO MANY ACRONYMS.

A close friend who spent twenty years in the Air Force recently gave me grief about the number of acronyms that seem to have taken over my vocabulary.

His point, to be fair, was not that acronyms are bad.

His point was that if you’re going to use one, you ought to know what it means.

This is a reasonable position.

Unfortunately, I work in healthcare.

We didn’t steal the military’s acronyms.

We developed an entirely separate infestation.

I am a CCBD credentialed through ADH, enrolled with DHS as a Medicaid provider after CMS approved the SPA, and I bill through MMIS using my NPI while worrying about HIPAA, BAAs, EFTs, EOBs, CEUs, CPR, CLC, IBCLC, CHW, UHC, BCBS, SMC, and whatever fresh alphabet soup crawled out of my inbox this morning.

Did you follow all of that?

Congratulations. Either you work in healthcare or you may be eligible for college credit.

And that’s before somebody goes into labor.

Birth work has its own dialect.

There are EDD, L&D, VBAC, TOLAC, ROM, PROM, AROM, EFM, EBB, and BRAIN, just for starters.

At some point we’re not communicating anymore.

We’re playing Scrabble without vowels.

The truly disturbing part is that I understand this stuff.

Someone can say something along the lines of, “The CCBD needs her NPI for MMIS after the CMS SPA approval, but check the EOB before asking DHS about the EFT,” and some horrible part of my brain goes:

Yes. Obviously.

Meanwhile, my close friend is staring at me like I’ve begun transmitting encrypted coordinates to NATO.

And sometimes those of us who work in healthcare and birth forget that normal people don’t speak this language.

An acronym slips into a conversation with a family, and suddenly we have to back up and translate what we just said into actual English.

That’s particularly important in birth work.

Families shouldn’t need a decoder ring to understand what is happening during pregnancy, birth, or postpartum care.

Part of a doula’s job is helping turn the alphabet soup back into language people can actually understand and use.

Because understanding matters.

You can’t meaningfully participate in a conversation when everyone else in the room seems to be speaking in abbreviations.

Acronyms are useful when everyone involved understands what they mean.

When they don’t, they’re just another barrier to understanding.

And part of a doula’s job is helping families get past those barriers.

Of course, while discussing this article with my twenty-year Air Force veteran friend, I made what I thought was a perfectly good joke and referred to all of this as my MOS.

That earned an immediate correction.

MOS is an Army term.

The Air Force uses AFSC.

Fine.

I stand corrected.

So the next time my close friend gives me grief about my alphabet soup, I have my answer ready:

“It’s my AFSC.”

AFSC: Air Force Specialty Code.

See?

Sometimes you really do have to explain the acronym.

Becoming an Arkansas Medicaid Doula Provider: From Midnight Coffee to ENROLLED

At 11:45 p.m. on August 31, 2026, the coffee was made.

The snacks were ready.

The bodies were exhausted.

But the demand was there. The need was there. And Arkansas Medicaid doula provider enrollment was scheduled to open at midnight.

So Danielle Wright and Annie Hill sat in their own kitchens and home office spaces, computers open and paperwork nearby, poised and ready to log into the Arkansas Medicaid provider enrollment system.

We were going to become Arkansas Medicaid doula providers.

We were prepared.

Or, more accurately, we thought we were prepared.

By about 1:00 a.m., it had become apparent that the application contained questions for which we simply did not yet have answers.

There comes a point in every great administrative adventure when another cup of coffee will no longer reveal the meaning of a government form.

We decided that perhaps the wisest course of action was to stop clicking things, get some sleep, and call Provider Enrollment in the morning.

September 1: Arkansas Medicaid Doula Enrollment Begins

Later that day, Annie and at least three other Certified Community-Based Doulas across Arkansas had submitted their Medicaid provider enrollment applications.

This was brand-new territory.

Arkansas Medicaid had never before enrolled Certified Community-Based Doulas as providers. The doulas applying were new to the system, the provider specialty was new, and everyone involved was learning how the process would work in practice.

We submitted our applications.

Then we waited.

Not for very long.

Because by September 2, we had learned a new acronym.

RTP: Return to Provider

RTP means Return to Provider.

If you have never encountered an RTP notice before, it means Medicaid received your application but found something it wanted corrected, clarified, added, or documented differently before enrollment could continue.

It is not the same thing as a denial.

It is more along the lines of:

We have your paperwork. We would like you to have your paperwork back for a moment.

The early applicants we were communicating with had all encountered some version of the same experience.

And thus began the next stage of becoming some of Arkansas’s first Medicaid-enrolled doulas.

We made phone calls.

We compared notes.

We reread the newly released provider materials.

We corrected applications.

We learned which documents needed to be submitted and how various portions of the application needed to be completed.

We called again.

And we discovered that perhaps the Medicaid enrollment portal should come with either chocolate or a complimentary stress ball.

Possibly both.  And maybe a set of the same for the poor people at AFMC who were to field our phone calls saying “we’ve read the existing documentation, but we have questions…”

Correct, Resubmit, Repeat

Annie’s application was corrected and resubmitted on September 3, 2026.

By this point, something else was becoming clear.

There was not going to be a well-worn path for us to follow because we were among the people making the path.

Arkansas’s Medicaid doula benefit was new.

Arkansas’s Certified Community-Based Doula credential was new.

The Medicaid provider enrollment process for doulas was new.

And when you are among the first people through a new system, sometimes you discover the places where the instructions, the portal, and reality do not quite line up yet.

Those discoveries may be frustrating at one in the morning, but they also make the process easier for the people who come next.

September 8: Learning How to Function as a Medicaid Provider

Annie Hill and Danielle Wright attending new provider training.On September 8, Annie and Danielle attended the Arkansas Medicaid New Provider Workshop.

Because becoming enrolled is only the first part.

Once Medicaid says yes, a provider still needs to understand how to function inside the Medicaid system.

That means learning about eligibility verification, documentation, claims, provider portals, billing requirements, covered services, and all the administrative machinery happening behind the scenes.

For Bright Blessings, learning those systems is important for a very simple reason:

Our families should not have to become Medicaid billing experts in order to receive doula care.

Their job is pregnancy.

Their job is preparing for birth.

Their job is recovering postpartum, learning their baby, feeding their baby, asking questions, making decisions, and caring for their families.

The provider paperwork?

That’s our job.

September 9: ENROLLED

Then came September 9, 2026.

Annie logged into the provider system.

And there it was.

ENROLLED.

After the midnight coffee, the application, the RTP, the corrections, the phone calls, the documentation, the resubmission, and a considerable amount of determined persistence, Annie Hill, Arkansas Certified Community-Based Doula #005, officially became an enrolled Arkansas Medicaid doula provider.

There may have been celebrating.

There may also have been a certain amount of staring at the screen just to make sure the word was still there.

It was.

ENROLLED.

Danielle Is Right Behind Her

Danielle Wright, Arkansas Certified Community-Based Doula #008, has been traveling the same road.

Her enrollment encountered additional issues that needed to be identified and corrected. Those problems have now been worked through, and her application has been submitted appropriately.

As of September 16, 2026, Annie has received her Medicaid provider enrollment approval, and we expect Danielle’s approval by Friday, September 18.

To the best of our knowledge as of this publication date, Annie may currently be the only Certified Community-Based Doula serving the Little Rock area whose Arkansas Medicaid provider enrollment has completed.

But Danielle should be right behind her.

And that matters, because Bright Blessings is not being built around one doula.

We are building an Arkansas doula collective.

That means expanding coverage, providing backup for one another, sharing experience, and creating a system in which more Arkansas families can receive consistent community-based doula care.

Arkansas Has a Very Small Number of Certified Community-Based Doulas

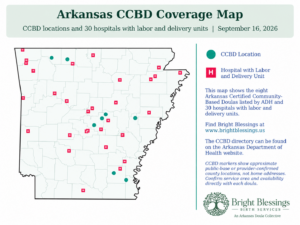
Arkansas map showing CCBD locations and hospitals with labor and delivery units, updated September 16, 2026.At the time this article was published in September 2026, the Arkansas Department of Health listed only eight Certified Community-Based Doulas statewide.

Not eight in Little Rock.

Not eight in Central Arkansas.

Eight across the entire state.

And the words Certified Community-Based Doula, or CCBD, matter.

A person can be a trained doula.

A person can hold certification from a national or independent doula organization.

A doula can be experienced, knowledgeable, and excellent at their work.

A doula can also work for a business or healthcare practice that participates in Medicaid for other services.

None of those things, by themselves, make that individual an Arkansas Certified Community-Based Doula.

For Arkansas Medicaid to reimburse doula services, the individual providing those services must hold the Arkansas CCBD credential and must separately complete Medicaid provider enrollment.

How Does a Doula Become Eligible to Provide Medicaid-Covered Doula Care?

There are two separate steps families should understand.

  1. The doula must become an Arkansas Certified Community-Based Doula, or CCBD. This credential is issued through the Arkansas Department of Health.
  2. The doula must complete Arkansas Medicaid provider enrollment. Holding a CCBD credential makes a doula eligible to pursue Medicaid enrollment, but certification alone does not mean Medicaid enrollment is complete.

Put simply:

CCBD certification first. Medicaid provider enrollment second.

This distinction matters when families are searching for an Arkansas Medicaid doula.

How Families Can Verify an Arkansas CCBD

A clinic, agency, group practice, healthcare organization, or other business may already participate in Arkansas Medicaid for completely unrelated services.

That does not automatically mean that every doula working for that organization is eligible to provide Medicaid-reimbursed doula care.

The credential belongs to the individual doula.

So how can families know?

Start with the Arkansas Department of Health’s official list of Certified Community-Based Doulas.

Look for the individual doula’s name.

If the person is not listed as an Arkansas CCBD, families should ask questions before assuming their doula services can be billed to Medicaid.

It is also important to remember that appearing on the CCBD list does not automatically mean Medicaid provider enrollment has been completed.

The Department of Health list verifies the CCBD credential.

Medicaid enrollment is the next step.

At Bright Blessings, we believe families deserve to know exactly who is providing their care, what credentials that person holds, and whether the services being offered are eligible for Medicaid reimbursement.

Why We Went Through All of This

It would be easy to tell this as a story about forms.

Or portals.

Or RTP notices.

Or staying awake until one o’clock in the morning wondering exactly what a particular box on an application was asking.

But none of those things are why we did it.

We did it because there are Arkansas families who have wanted doula support and simply could not afford to pay for it privately.

We did it because geography and income should not determine whether someone has access to knowledgeable support during pregnancy, labor, birth, and postpartum.

We did it because community-based doulas can help families navigate an increasingly complicated maternity care system.

We did it because families deserve someone who has time to listen.

And we did it because Arkansas Medicaid families now have a benefit that can make that support accessible without asking families already stretching their budgets to somehow find hundreds or thousands of additional dollars for doula care.

Medicaid Doula Care in Little Rock, Searcy, Conway, and Central Arkansas

Bright Blessings Birth Services supports families experiencing both low-risk and high-risk pregnancies.

Our collective serves families throughout Central Arkansas, including Little Rock, Cabot, Jacksonville, Beebe, Searcy, Conway, Lonoke, and surrounding communities.

Our doulas provide nonmedical emotional, physical, informational, practical, and advocacy support throughout pregnancy, labor, birth, and postpartum.

And now we can begin bringing that support to Arkansas Medicaid families who may never before have been able to afford professional doula care.

The Midnight Coffee Was Worth It

On August 31, two exhausted doulas sat in two different homes with coffee, snacks, computers, and absolutely no idea how many times we were about to learn the phrase Return to Provider.

A little more than a week later, the first Bright Blessings doula was officially enrolled.

The second is right behind her.

We learned the system.

We found the problems.

We corrected the applications.

We asked questions.

We kept going.

And perhaps most importantly, the next person through the process will know a little more because those first Arkansas CCBDs went through it first.

That is how new systems become usable.

One question, one correction, one provider, and apparently one pot of coffee at a time.

Bright Blessings Is Now Accepting Arkansas Medicaid Families

Bright Blessings Birth Services is now accepting Medicaid clients.

If you are pregnant and covered by Arkansas Medicaid and are interested in working with a doula, please contact us.

If you are a physician, midwife, nurse, social worker, community organization, church, pregnancy resource provider, public health professional, or anyone else working with pregnant Arkansas families, please share the word.

Families who may never before have been able to afford professional doula support may now have access to it through Arkansas Medicaid.

We look forward to working with them.

Bright Blessings Birth Services
An Arkansas Doula Collective
501-300-5841
brightblessings.us

What We’ve Been Building While the Journal Was Quiet

If you have been watching the Bright Blessings Journal, you may have noticed that it has been quiet since August 29. That is not because there has been nothing to say. It is because almost all of our available time has gone into the work itself.

The first two weeks of September brought the beginning of Arkansas Medicaid coverage for doula care, the last stages of provider enrollment, training, new systems, new clients, and the continuing work of turning Bright Blessings from a solo practice into an Arkansas doula collective.

Arkansas Medicaid doula care is here

On September 1, Arkansas Medicaid’s new Supportive Maternal Care benefit became effective. I submitted my provider enrollment application that morning, worked through a returned application and its requested corrections, and received confirmation on September 9 that I am officially enrolled as an Arkansas Medicaid provider.

This matters far beyond an identification number. It means Bright Blessings can now accept Arkansas Medicaid clients for covered doula services under the new benefit. It also means that the months spent following legislation, attending meetings, reading manuals, asking questions, and preparing our systems have moved into actual client care.

We have already begun moving Medicaid inquiries into active care. Because the benefit requires at least one in-person visit, we are building our scheduling and intake process around both compliance and the practical needs of Arkansas families. Our lead forms, contracts, insurance-card collection, documentation, and appointment workflow have all needed attention at once.

You can learn more on our Arkansas Medicaid Doula Care page.

Preparing as a team

Annie Hill and Danielle Wright attending new provider training.Danielle Wright and I attended the Arkansas Medicaid New Provider Workshop together on September 8. The photograph with this post was taken that day. It represents a great deal more than sitting beside one another at a training. It is part of the work of building shared knowledge, dependable backup, and a collective that can serve families across Central Arkansas without placing everything on one doula.

Danielle has been added to our practice system, and we are building the procedures that allow inquiries to be assigned appropriately while keeping records, privacy, scheduling, and client communication consistent. Paula Branam and Renee Bertot are also continuing their student pathways as Bright Blessings grows the next layer of the team.

That kind of growth is not especially glamorous from the outside. It looks like agreements, forms, calls, training, careful decisions, and a surprising number of small technical changes. It is still the foundation that makes reliable care possible.

There has been public work, too

During these same two weeks, Arkansas news coverage began helping families understand that Medicaid doula care is becoming available. I have continued conversations with maternal-health leaders, health plans, hospitals, community partners, and other doulas about how this new benefit will work in practice.

We have also been updating the Bright Blessings website, bringing our team information forward, changing our public language from waiting for Medicaid enrollment to accepting Medicaid clients, and preparing for upcoming community events. Behind that is ongoing work on Learn to Doula Village and the training systems needed by doulas who want to enter this field prepared for both community care and the realities of professional practice.

So, why were we quiet?

Because we were building.

Bright Blessings is entering a different stage now. We are no longer only preparing for Arkansas Medicaid doula coverage. We are providing care within it. We are no longer talking abstractly about becoming a collective. We are putting the people, systems, and expectations in place to function as one.

There will be more to share as this work develops. For now, if you are pregnant, have Arkansas Medicaid, and are looking for doula support in our service area, you can schedule a clarity call to begin.

Exciting news for maternal health and rural families across Arkansas

The Doula Alliance of Arkansas has been awarded $860,500 through Arkansas’s Rural Health Transformation Program for Access Starts at Home: Rural Maternal Care Coordination and Doula Support.

The program will place 10 certified doulas in partner clinics across Northwest, North Central, Upper Delta, Lower Delta, and Southwest Arkansas, helping connect families, doulas, and clinical care teams throughout pregnancy and through six months postpartum. The program will also work in partnership with MySwaddle to help strengthen that connection and continuity of support.

For families living in rural communities, access matters. Distance, transportation, limited local resources, and fewer maternity-care options can all create additional barriers during pregnancy and postpartum. Bringing community-based doula support closer to families is one more way to help bridge those gaps.

Doulas from Bright Blessings Birth Services will be represented at this year’s annual Doula Alliance of Arkansas Conference in Pine Bluff, and we’re looking forward to hearing much more about Access Starts at Home, how the program will be implemented in Arkansas communities, and the role MySwaddle will play in supporting families and care coordination.

Congratulations to the Doula Alliance of Arkansas, and especially to the rural Arkansas families who will ultimately benefit from this investment in maternal health.

#ArkansasDoulas #CommunityBasedDoula #RuralMaternalHealth #MaternalHealth #DoulaSupport #BrightBlessingsBirthServices #DoulaAllianceOfArkansas #ArkansasMaternalHealth

Related: Meet the Bright Blessings team and explore our birth doula support.

A Doula’s View from the 2026 Arkansas Maternal Health Roundtable

Bright Blessings blog graphic for A Doula's View from the 2026 Arkansas Maternal Health Roundtable

What I heard, what was missing, and what Arkansas must do next

By Angela “Annie” Hill, Arkansas Department of Health Certified Community-Based Doula #005 August 23, 2026

I have had two full days to process what I heard at the 2026 Arkansas Maternal Health Roundtable, held Thursday, August 20, at the William J. Clinton Presidential Library and Museum in Little Rock.

I did not want to rush directly from the presentations and conversations into a tidy event recap. There was too much information, too much progress, and too much still unfinished.

The Roundtable made one thing unmistakably clear: Arkansas is finally putting serious attention, funding, policy, and institutional effort behind its maternal health crisis.

It also made some of the gaps in that work painfully visible.

I left encouraged by the programs being built, the policies moving forward, and the people clearly committed to making them work. I also left with a question that has continued to bother me:

Who was not in the room?

I Was in the Room Where It Happened

To borrow briefly from Hamilton, I was in the room where it happened.

But I was not there because anyone had made a point of ensuring that an actual Arkansas Certified Community-Based Doula, certified by the Arkansas Department of Health, had a seat in that room.

I was there because I had been savvy enough to set up online alerts for legislative activity, maternal health policy, Medicaid developments, and other events affecting my profession. That is how I learned about the Roundtable. I registered myself and showed up.

That distinction matters.

I am Arkansas’s fifth ADH-certified Community-Based Doula. I am also a retired home birth midwife with decades of experience supporting families during pregnancy, birth, and postpartum recovery.

Because of that background, another absence was impossible for me to overlook.

Practicing home birth midwives were not represented at all.

Although much of the Roundtable centered on hospital-based care, Arkansas’s maternal health crisis does not begin and end at hospital doors.

If Arkansas is serious about improving maternal health outcomes, this work will require all hands on deck. That means intentionally including the doulas, home birth midwives, community health workers, lactation professionals, emergency medical providers, rural healthcare workers, and other professionals already working directly with families in their homes and communities.

The people expected to help carry these solutions into practice should not have to stumble across the conversations where those solutions are being shaped.

Policy Is Only the Beginning

One message surfaced repeatedly throughout the Roundtable: passing a law or creating a program is not the same as changing an outcome.

Implementation matters.

Enrollment matters.

Reimbursement matters.

Communication matters.

Families knowing that a service exists matters.

Providers knowing how to deliver and bill for that service matters.

Collaboration cannot be “one and done.” It has to continue after the legislation passes, after the press release is issued, and after everyone leaves the Roundtable.

That message could not have been more timely.

While maternal health leaders were gathering at the Clinton Presidential Library, Arkansas was also moving the Medicaid rules for doula care across the legislative finish line. Arkansas Medicaid coverage for certified doula services is scheduled to begin September 1.

That is an enormous step forward for Arkansas families.

It is also the beginning of implementation, not the end.

Coverage on paper does not help a pregnant person unless certified doulas can enroll as Medicaid providers, managed care organizations are prepared to work with us, billing systems function correctly, healthcare teams understand our role, and families can find doulas who are actually available to serve them.

The state has opened the door. Now we have to build the pathway through it.

I will be writing much more about what Arkansas Medicaid doula coverage means for families, how Certified Community-Based Doulas become eligible to provide covered services, and what still needs to happen before this new benefit works smoothly in real life.

Pregnancy Does Not End at Delivery

Another major theme was postpartum care.

Pregnancy does not end when the baby is delivered, and maternal health risks do not disappear when a family leaves the hospital.

I was encouraged to hear about efforts such as Arkansas’s Proactive Postpartum Call Center, which contacts participating patients after hospital discharge to discuss recovery, identify warning signs, and connect families with appropriate care and community resources.

That kind of proactive outreach matters.

It also demonstrates why continuity of care is so important. A postpartum patient may be exhausted, overwhelmed, frightened, unsure whether a symptom is normal, or unaware that something warrants immediate medical attention. They may not know whom to call, how urgently to call, or how to explain what is happening.

A doula does not replace a nurse, midwife, physician, mental health professional, or emergency medical provider.

We can, however, help a family recognize that something needs attention, organize the information they need to communicate, and reach the appropriate healthcare professional promptly.

A statewide call center can provide an important layer of support. So can a trusted person who already knows the family, understands their circumstances, and has been checking on them throughout pregnancy and postpartum recovery.

Arkansas needs both.

Rural Communities Need More Support, Not Less

Rural maternal healthcare was woven throughout the day’s discussions, and it must remain central to whatever Arkansas builds next.

According to the March of Dimes maternity care access data for Arkansas, 50.7 percent of Arkansas counties are considered maternity care deserts.

When a community loses its birthing hospital or has no local obstetric provider, pregnant families must travel farther for prenatal appointments, monitoring, birth, and postpartum care. Transportation, work schedules, childcare, fuel costs, weather, and simple geography become healthcare barriers.

The absence of a hospital does not make a doula less relevant.

It makes community-based doula support even more critical.

A doula cannot replace a hospital, physician, certified nurse-midwife, home birth midwife, ambulance, or emergency department. What a doula can do is help bridge the growing distance between a family and the healthcare system.

We can help families prepare for appointments, identify barriers before they become crises, understand when they need to contact their healthcare team, locate resources, and make realistic plans for reaching care.

Mobile clinics, telehealth, transportation programs, community health workers, and doulas can all help build maternal health infrastructure where traditional infrastructure has disappeared.

But those solutions will only work if the people delivering them are included in the planning.

Trusted Information Is Maternal Health Infrastructure

The Roundtable also addressed something every doula and healthcare professional is already encountering: families are receiving pregnancy information from TikTok, Facebook, Instagram, YouTube, and online parenting groups long before they walk into a medical office.

Some of that information is excellent.

Some of it is incomplete, misleading, or dangerous.

Dr. Fran’s presentation about social media, trust, and pregnancy misinformation has stayed with me, and it deserves far more than a paragraph inside this article. Paging Dr. Fran will become its own continuing series because the subject is too large and too important for a single post.

Families are going to seek information online whether professionals approve of it or not.

Ridiculing people for what they have heard or frightening them into silence will not build trust. It may only guarantee that they stop telling their healthcare providers what they are thinking, reading, or considering.

The answer is credible, understandable information paired with respectful conversation.

Doulas can help with that, too.

We have time to listen to the question behind the question. We can help clients identify reliable sources, prepare questions for their healthcare providers, and understand that informed decision-making requires both accurate information and meaningful conversation with the professionals responsible for their medical care.

Trust is not an optional extra in maternal healthcare.

Trust is part of the infrastructure.

ACOG Says Doulas Matter

The importance of including doulas in maternal healthcare is not merely something doulas say about ourselves.

In 2026, the American College of Obstetricians and Gynecologists published new guidance on partnering with doulas in clinical settings.

ACOG’s guidance recognizes that strong doula-clinician partnerships can improve communication, continuity, patient-centered care, and the experience and outcomes of the families being served. It calls on obstetric professionals to understand the doula’s scope and create respectful, collaborative teams.

Arkansas is already taking steps in that direction. The UAMS Institute for Community Health Innovation has developed the Advancing Doulas and Perinatal Teams Toolkit to help hospitals and doulas work together more effectively.

That collaboration is essential because doulas and clinicians do different jobs.

Doulas are nonmedical professionals. We do not diagnose conditions, prescribe treatment, perform clinical procedures, or replace healthcare providers. We do not make decisions for our clients.

Our work is relational and continuous.

We spend time with families. We learn what is normal for them. We provide education, practical preparation, emotional support, physical comfort, and help navigating systems that can be confusing even under the best circumstances.

We help clients prepare questions and communicate concerns clearly. We reinforce the importance of contacting their medical team when something does not feel right. We help them understand when an issue has moved beyond the doula’s scope and needs to be handled by the appropriate healthcare professional.

In other words, we help connect the family to the medical system before a concern becomes an emergency.

This Must Be an All-Hands-on-Deck Effort

I do not want the gaps I observed to erase the value of the Roundtable.

Important work is happening in Arkansas. People in state government, hospitals, universities, public health agencies, nonprofit organizations, and community programs are investing real time and effort into improving maternal health.

I left the Clinton Presidential Library with more hope than I carried into it.

But hope does not excuse us from examining who was missing.

Representation is not ceremonial. It directly affects which problems are recognized, which solutions are considered, and whether those solutions will work outside conference rooms, hospitals, and government offices.

Hospital administrators bring essential institutional knowledge.

Physicians, nurses, and midwives bring clinical expertise.

Public health officials bring data and statewide planning.

Community health workers bring local knowledge and resource navigation.

Home birth midwives bring experience caring for families beyond hospital walls.

Doulas bring continuity, trust, education, and direct knowledge of what families encounter between appointments.

Families themselves bring lived experience that no professional can substitute for.

Arkansas needs all of those perspectives.

We cannot wait for a frightened pregnant person or newly postpartum parent to become sick enough, loud enough, or desperate enough for the system to notice them.

How else are we supposed to catch concerns early, help families communicate and escalate them appropriately, and get the right healthcare professionals involved before those concerns become emergencies?

At Bright Blessings, we often say:

We do not catch babies. We catch problems before they become emergencies.

To do that work effectively, doulas need access, collaboration, sustainable reimbursement, and intentional inclusion in the systems Arkansas is building.

We need a seat at the table.

And doulas belong in the room.

More Than Showing Up: The Logistics of Doula Work

At the end of May, I sat down with Katherine Stephens of Made For Birth for a conversation I have wanted families, new doulas, and even experienced birth workers to hear. As an Arkansas Certified Community-Based Doula, doula trainer, and retired home birth midwife, I wanted to make the work behind doula care visible.

What does it actually take for a doula to be available when a client goes into labor at 2 a.m., on a holiday, or several weeks earlier than expected?

The answer is much more than showing up.

Episode 115 of the Made For Birth podcast, “More Than Showing Up: The Logistics of Doula Work with Annie Hill,” was released on August 14. Katherine and I talked in depth about the work families see, the work they never see, and what allows a doula to offer skilled, ethical, dependable support over the long term.

A doula is not simply a supportive friend

Emotional reassurance, encouragement, cool washcloths, position changes, and hands-on comfort all matter. They are part of doula care, but they are not the whole of it.

An experienced doula also brings critical thinking, communication skills, birth education, advocacy tools, professional boundaries, and the ability to remain steady when a family feels overwhelmed.

A doula is not a miniature midwife. We do not diagnose, perform clinical assessments, or make medical decisions for our clients. We are a nonclinical bridge between the family and the clinical care team. We help families understand what they are hearing, identify the questions they want to ask, and remain active participants in their own care.

The work begins long before labor

In the episode, I describe preparing individualized educational materials for a client who wanted to understand her options but became overwhelmed when given too many choices at once. Good support is not measured by how much information a doula can pour onto someone. It is measured by whether the information is useful, understandable, and matched to that family’s actual needs.

Prenatal doula work can include:

  • Learning how a client processes information and makes decisions
  • Preparing the partner to take an active, confident role
  • Attending a prenatal appointment when that support would help
  • Explaining birth terminology and common procedures in plain language
  • Practicing questions a client may want to ask the care team
  • Planning for labor, postpartum recovery, feeding, visitors, and household support
  • Building backup coverage before it is ever needed

As I said during the interview, “A good doula will educate and empower.” The goal is not to make a family dependent upon me. The goal is to help them feel informed, grounded, and capable of using their own voice.

Recognition is not diagnosis

One of the most important distinctions in doula work is the line between recognizing a concern and diagnosing a condition.

At Bright Blessings, we often say, “We don’t catch babies; we catch problems before they become emergencies.” That does not mean practicing medicine. It means listening carefully, recognizing when something deserves prompt attention, and encouraging the client to contact the appropriate healthcare professional.

A skilled doula knows how to say, “This may be worth discussing with your provider,” without turning concern into panic. We help clients communicate what they are experiencing and make sure the clinical team has the opportunity to evaluate it.

Doulas support partners, too

A doula is not there to replace a spouse or partner. We help partners understand what is happening, give them practical ways to support the laboring person, and step in where they need information, reassurance, rest, or another pair of hands.

Sometimes that means teaching a hip squeeze. Sometimes it means helping a partner recognize that the family wants more information before making a decision. Sometimes it means quietly reminding both people that they have time to breathe and ask another question.

Sustainability is part of ethical care

The episode also addresses something birth work does not discuss honestly enough: a calling still needs a sustainable structure.

Reliable doula care requires on-call planning, backup doulas, childcare and family arrangements, transportation, continuing education, protected health information practices, contracts, documentation, insurance credentialing, billing systems, and fees that allow the doula to remain in practice.

It also requires rest, peer support, appropriate debriefing, and a life outside birth work. Burned-out doulas cannot provide the steady presence families deserve. Taking care of our own physical, emotional, and financial needs is not selfish. It is part of maintaining safe, dependable care.

This interview was recorded while Arkansas was still building the systems needed to put Act 965 into practice. Some administrative details have continued to move since our conversation, but the central issue has not changed. Access to doula care must expand, and the doulas providing that care must be able to sustain the work.

Maternal sovereignty is the foundation

Near the end of our conversation, Katherine asked me to explain the Maternal Sovereignty Method.

At its core, it is active listening followed by thoughtful implementation. It begins with recognizing that the client is a sovereign person. Her values, history, nervous system, family, risks, hopes, and decisions belong at the center of her care.

Informed consent is not a form someone signs. It is an ongoing process of receiving understandable information, asking questions, considering options, and making a voluntary decision.

That is the work beneath the visible work. It is why doula care is more than showing up.

Listen to the conversation

Listen to Episode 115, “More Than Showing Up: The Logistics of Doula Work with Annie Hill,” on Made For Birth. The episode is also available through Apple Podcasts and Spotify.

If you are pregnant in Central or North Central Arkansas and want to talk about what skilled doula support could look like for your family, visit Bright Blessings Birth Services to schedule a clarity call.

Angela “Annie” Hill

Owner, Bright Blessings Birth Services

Arkansas Department of Health Certified Community-Based Doula #005

Related: Meet the Bright Blessings team and explore our birth doula support.

What does it mean to be a CCBD?

What does it mean to be a Community-Based Doula?

It means knowing that supporting a family sometimes extends beyond preparing for birth.

A community-based doula knows her community. She knows where to turn when a family needs transportation, food assistance, childbirth education, lactation support, housing resources, mental health services, help navigating healthcare, or support beyond her own scope of practice.

We aren’t expected to solve every problem. We shouldn’t.

But we should know how to help families find the people and resources that can.

At Bright Blessings Birth Services, doula care isn’t about deciding what choices a family should make. It’s about education, connection, advocacy, and making sure families have the information and support they need to make their own informed decisions.

That’s what the community in community-based doula care means to us.

Related: Meet the Bright Blessings team and explore our birth doula support.

Why Choose a Doula in Arkansas?

A doula holding hands with a pregnant person.Pregnancy and birth are not medical emergencies by default.
They are profound, physiological life events that deserve skilled support, informed decision-making, and respectful care.

For families in Arkansas, choosing a doula is not just about comfort. It is about safety, education, and advocacy in a maternity care system that is under strain.

Arkansas Birth Statistics Tell a Story

In Arkansas, approximately 34 percent of births are delivered by cesarean section, a rate higher than both national and evidence-based recommendations. While cesarean birth can be lifesaving when medically necessary, high intervention rates are also associated with increased risks for mothers, longer recovery times, and higher complication rates in future pregnancies.

Arkansas also ranks among the states with the highest maternal mortality rates in the country. Many pregnancy-related deaths have been found to be preventable. Rural families face particular challenges, including long travel distances to hospitals with labor and delivery units and limited access to higher-level care when complications arise.

These realities mean that many Arkansas families enter pregnancy and birth without consistent education, without enough time with their providers, and without someone solely focused on their well-being.

Why This Matters for Arkansas Families

Most prenatal visits are short. Important questions may go unanswered. Concerns may be unintentionally minimized, not because providers do not care, but because the system is stretched thin.

Without adequate education and support, families may not fully understand:

  • What is normal in pregnancy and labor

  • When intervention is truly necessary

  • What informed consent actually means

  • How to communicate concerns effectively in a hospital setting

This gap in care contributes directly to poor maternal outcomes.

What a Doula Does

A doula is a trained, non-medical birth professional who provides continuous emotional, physical, and educational support throughout pregnancy, labor, birth, and the postpartum period.

A doula helps Arkansas families:

  • Prepare for pregnancy and birth with evidence-based education

  • Understand medical options and terminology

  • Navigate hospital birth, homebirth, or birth center care

  • Reduce fear and stress during labor

  • Improve communication with doctors, midwives, and nurses

  • Feel supported, heard, and respected

Research consistently shows that families who work with a doula experience lower cesarean rates, fewer medical interventions, shorter labors, and higher satisfaction with their birth experience.

Doula Support and Medical Care Work Together

Choosing a doula does not mean rejecting obstetric or neonatal care.

High-level medical care is essential when complications arise. The issue is not the existence of advanced care, but the assumption that intervention must be the default rather than the appropriate response.

Doulas support families in understanding risk, recognizing when escalation is needed, and remaining grounded and informed if that escalation occurs. This partnership improves safety, not risk.

A Local Solution to a Statewide Problem

For most of human history, pregnancy and birth were supported by knowledgeable attendants who provided education, reassurance, and skilled presence. Modern doulas carry forward that role while working within today’s medical system.

In a state like Arkansas, where access to maternity care is uneven and outcomes continue to lag, doula care is a protective factor. Listening saves lives. Education reduces risk. Support changes outcomes.

At Bright Blessings, we believe no one should navigate pregnancy or birth alone.

Serving Central Arkansas Families

Bright Blessings Birth Services provides professional doula care and pregnancy support for families across Central Arkansas, including Cabot, Little Rock, Conway, Beebe, Searcy, and surrounding areas in Lonoke, Pulaski, Faulkner, and White counties.

Ready to Learn More?

If you are pregnant, planning a pregnancy, or supporting someone who is, you deserve care that listens first and supports fully.

? Contact Bright Blessings today to learn how doula support can help you approach pregnancy and birth with confidence, knowledge, and peace of mind.

Learn more about doula support

For clinical context, read ACOG’s guidance on partnering with doulas. Explore Bright Blessings doula services and choose your consultation path.